
Visual Pathway Anatomy
Curriculum lesson · updated 2026-07-30
Pending review from section expertOn this page
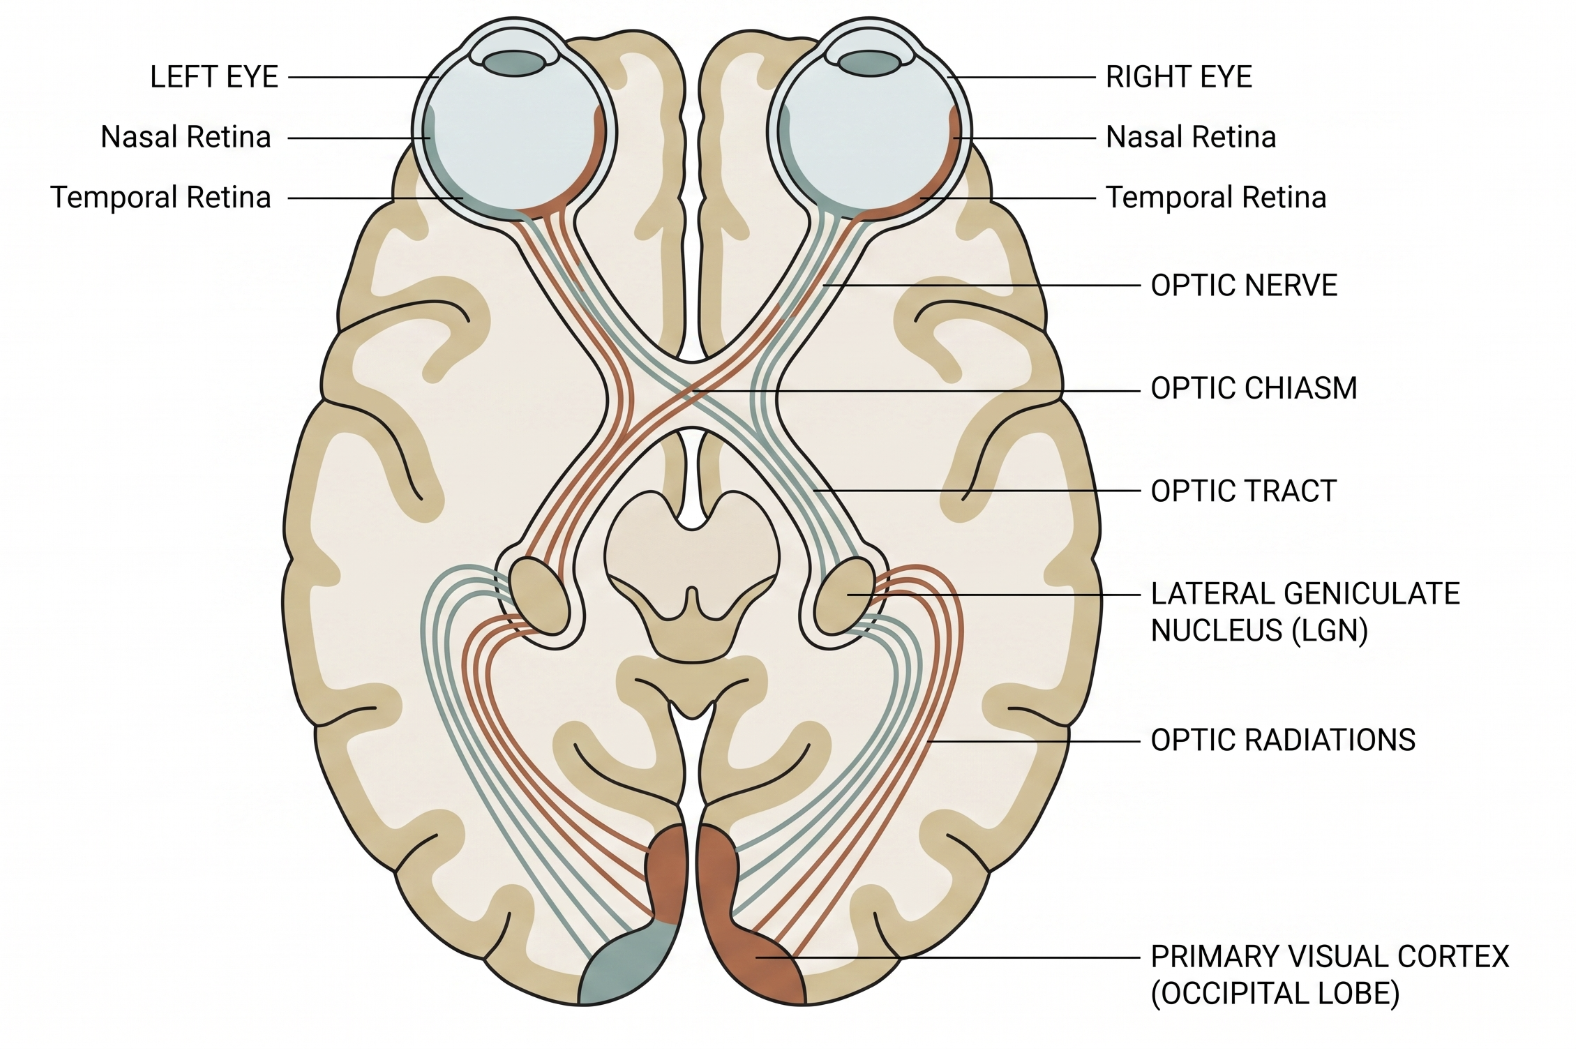
The visual pathway carries information from the retina to the occipital cortex through a precisely organized sequence: retina, optic nerve, optic chiasm, optic tract, lateral geniculate nucleus (LGN), optic radiations, and primary visual (striate) cortex.1 Each optic nerve carries retinal ganglion cell axons from one eye to the chiasm, where nasal-retina axons (serving temporal visual field) decussate to the opposite side while temporal-retina axons (serving nasal visual field) remain uncrossed. This partial decussation is why chiasmal lesions (classically pituitary tumors) characteristically produce bitemporal visual field defects, while lesions posterior to the chiasm produce homonymous (same-sided) defects in both eyes.2 Beyond the chiasm, each optic tract carries crossed and uncrossed fibers representing the same contralateral hemifield from both eyes, synapsing at the LGN. From the LGN, optic radiations fan toward the occipital cortex — superior radiation fibers (inferior visual field) pass through the parietal lobe, while inferior radiation fibers (superior visual field, Meyer's loop) sweep through the temporal lobe before turning posteriorly, explaining why temporal versus parietal lesions produce different quadrant patterns of homonymous field loss.2 The pathway terminates at the retinotopically organized primary visual cortex.
Because each anatomic waypoint has a distinct, reproducible relationship to the visual field, correlating a patient's field defect pattern with expected lesion location is a core localizing skill.1 Structural imaging can visualize downstream consequences of pathway injury, including transsynaptic degeneration of the anterior visual pathway following an acquired retrogeniculate lesion — showing the pathway is functionally interconnected across relay points rather than a series of independent segments.2 Beyond conscious visual perception, retinal ganglion cell output also feeds a parallel pathway mediating the pupillary light reflex, which diverges from the conscious visual pathway near the midbrain rather than continuing to occipital cortex — explaining why a lesion can selectively impair vision without affecting pupillary function, or vice versa, depending on where it interrupts these related but distinct pathways.1
- Bitemporal hemianopia localizes classically to the optic chiasm (e.g., pituitary macroadenoma) because only decussating nasal-retina fibers are affected2
- Homonymous field defects localize posterior to the chiasm, in the optic tract, radiations, or occipital cortex2
- A superior homonymous quadrantanopia suggests a temporal lobe lesion (Meyer's loop), while an inferior homonymous quadrantanopia suggests a parietal lobe lesion2
- Correlating structural imaging with visual field deficits and pupillary abnormalities is central to diagnosing, localizing, and monitoring neurologic disease affecting vision1
- The optic chiasm's partial decussation is the single anatomic fact explaining the bitemporal-versus-homonymous distinction2
- Incongruous homonymous field defects suggest a more anterior retrochiasmal lesion (optic tract), while highly congruous defects suggest an occipital lesion
- Meyer's loop's course through the temporal lobe explains why temporal lobe lesions classically produce superior quadrant field loss
- The pupillary light reflex pathway diverges from the conscious visual pathway near the midbrain, so vision and pupillary function can be dissociated depending on lesion location1
- Common pitfall: assuming any visual field defect localizes to the eye itself rather than considering the entire retina-to-cortex pathway
- Common pitfall: confusing bitemporal (chiasmal) with homonymous (retrochiasmal) field loss, which point to fundamentally different lesion locations2
- Common pitfall: forgetting pupillary and visual field findings can be dissociated because their pathways diverge before the cortex1
Visual Pathway: Lesion Location to Field Defect
Clinical Skills for This Topic
Performing formal visual field testing →
Characterize field defect patterns (bitemporal vs. homonymous, congruous vs. incongruous) to localize a lesion along the visual pathway.
Checking pupillary responses alongside visual function →
Determine whether a lesion affects the conscious visual pathway, the pupillary pathway, or both, based on their anatomically distinct courses.
Correlating field defect pattern with expected imaging findings
Predict likely lesion location (chiasm, tract, radiation, occipital cortex) before reviewing neuroimaging.
Practice Questions
Question 1 of 6
Score: 0/0
What anatomic event at the optic chiasm explains the difference between bitemporal and homonymous visual field defects?
Saved in this browser.