
Physiologic Optics of the Eye
Curriculum lesson · updated 2026-07-30
Pending review from section expertOn this page
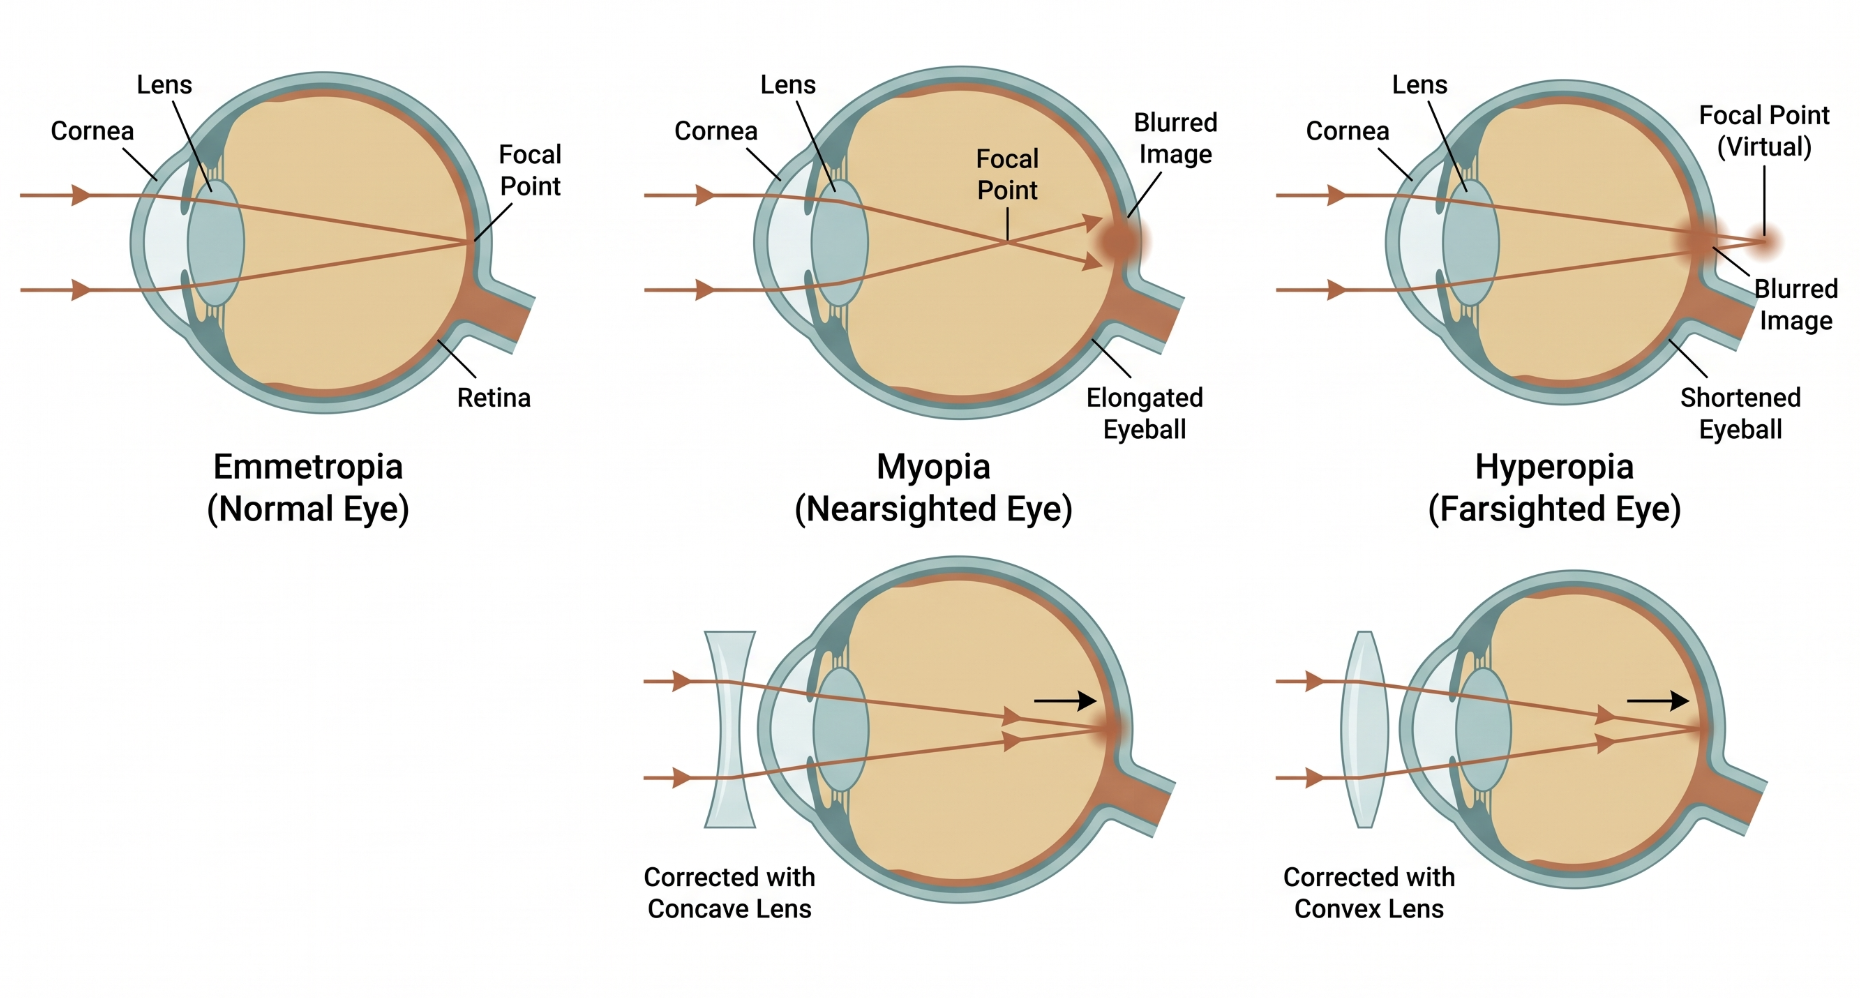
Refractive status is the net result of four optical components acting together: corneal curvature, crystalline lens power, axial length (cornea to retina), and the refractive indices of the ocular media. No single structure determines refractive status alone — a given axial length can be emmetropic, myopic, or hyperopic depending on how well it matches the eye's total focusing power. Light is refracted at each interface it crosses: the cornea provides roughly two-thirds of total refractive power (from the large refractive-index difference between air and the tear film/cornea), while the crystalline lens supplies the rest and can actively reshape itself to add power for near focus (accommodation). When the combined refractive power of cornea and lens is mismatched to axial length, the image forms in front of (myopia) or behind (hyperopia) the retina instead of on it.
During childhood, eyes do not simply grow at a fixed rate — a visual feedback process called emmetropization actively coordinates axial growth with optical power, nudging most developing eyes toward a well-focused state. The retina detects the sign and magnitude of optical defocus and generates signals regulating the rate of axial elongation. An emerging "eye-brain axis" perspective proposes that retinal neurotransmitter signaling (including dopaminergic pathways) and broader visual-cortex maturation/neuroplasticity participate in this feedback loop, integrating behavioral factors like sleep, near-viewing habits, and outdoor light exposure into the pathways governing eye growth.1 This "brain-centric" framing is a clinically integrative model rather than a claim that post-retinal processing is required for basic emmetropization, and evidence that neural changes consistently precede (rather than accompany) refractive error remains limited, with causal direction not firmly established.1
When emmetropization does not fully correct a mismatch, or axial length outpaces optical power during growth, myopia results and tends to progress as the eye continues to elongate through childhood and adolescence. In adulthood, the crystalline lens progressively stiffens, reducing accommodative amplitude for near focus — the optical basis of presbyopia (see the Lens Anatomy & Physiology lesson for cellular detail).
Axial length and spherical equivalent refraction (SER) capture different aspects of a mismatched optical system and carry different clinical information.2 Normal axial length varies substantially with age, sex, height, and ethnicity, while SER shows much weaker dependence on these factors, and only a small tail of emmetropic eyes ever reach commonly cited "high-risk" axial length thresholds (e.g., ≥26mm).2 Retinal pathology risk rises steeply with increasing axial length, but this long-eye threshold applies to fewer than 10% of eyes overall; SER-defined moderate/high myopia better captures the cataract and primary open-angle glaucoma risk gradients that most myopic patients will actually encounter across the broader myopic range.2 This supports using SER as the primary metric for monitoring myopia progression and risk in most children, reserving axial length for selectively identifying the minority with greater axial elongation.2
- Refractive status depends on the match between total optical power (cornea + lens) and axial length, not on any one component alone
- Emmetropization is an active, visually guided feedback process during childhood, not simply passive eye growth1
- Spherical equivalent refraction, not axial length alone, better reflects cataract and glaucoma risk gradients across the myopic range most patients reach2
- Axial length thresholds (e.g., ≥26mm) reliably flag a small subset of eyes at markedly higher retinal risk, but this applies to a minority of myopic eyes2
- Common pitfall: treating axial length as a universal proxy for myopia-related risk across all outcomes, when SER better predicts cataract/glaucoma risk for most patients2
- Common pitfall: overstating the eye-brain axis model of myopia as an established causal mechanism rather than an evolving, largely associative reframing1
- Common pitfall: assuming a given axial length is inherently pathologic without considering it relative to total refractive power
Refractive Components & Emmetropization Feedback
Clinical Skills for This Topic
Performing manifest and cycloplegic refraction
Determine spherical equivalent refraction as the primary metric for characterizing and monitoring refractive status.
Interpreting axial length measurements (biometry)
Use axial length selectively to flag eyes with significant elongation and higher retinal risk, rather than as a universal risk metric.
Correlating refractive findings with retinal and lens exam findings →
Connect a patient's refractive status to expected structural findings (e.g., myopic fundus changes, lens curvature) on dilated exam.
Practice Questions
Question 1 of 6
Score: 0/0
What determines an eye's refractive status (emmetropia, myopia, or hyperopia)?
Saved in this browser.
References
- [1]Capobianco M, Nicolosi SG, Dammino E, Cappellani F, Khouyyi M, D'Esposito F, Gagliano C, Zeppieri M. Neuro-ophthalmic review on pediatric myopia: Advancing from refraction to a brain-centric model of axial growth. World Journal of Clinical Pediatrics. 2026.
- [2]Clark RA, Wong RK. Spherical Equivalent Refraction Versus Axial Length for Monitoring Childhood Myopia and Estimating Disease Risk: A Systematic Review and Meta-Analysis. American Journal of Ophthalmology. 2026.