
Fungal Keratitis
Curriculum lesson · updated 2026-07-29
Pending review from section expertOn this page
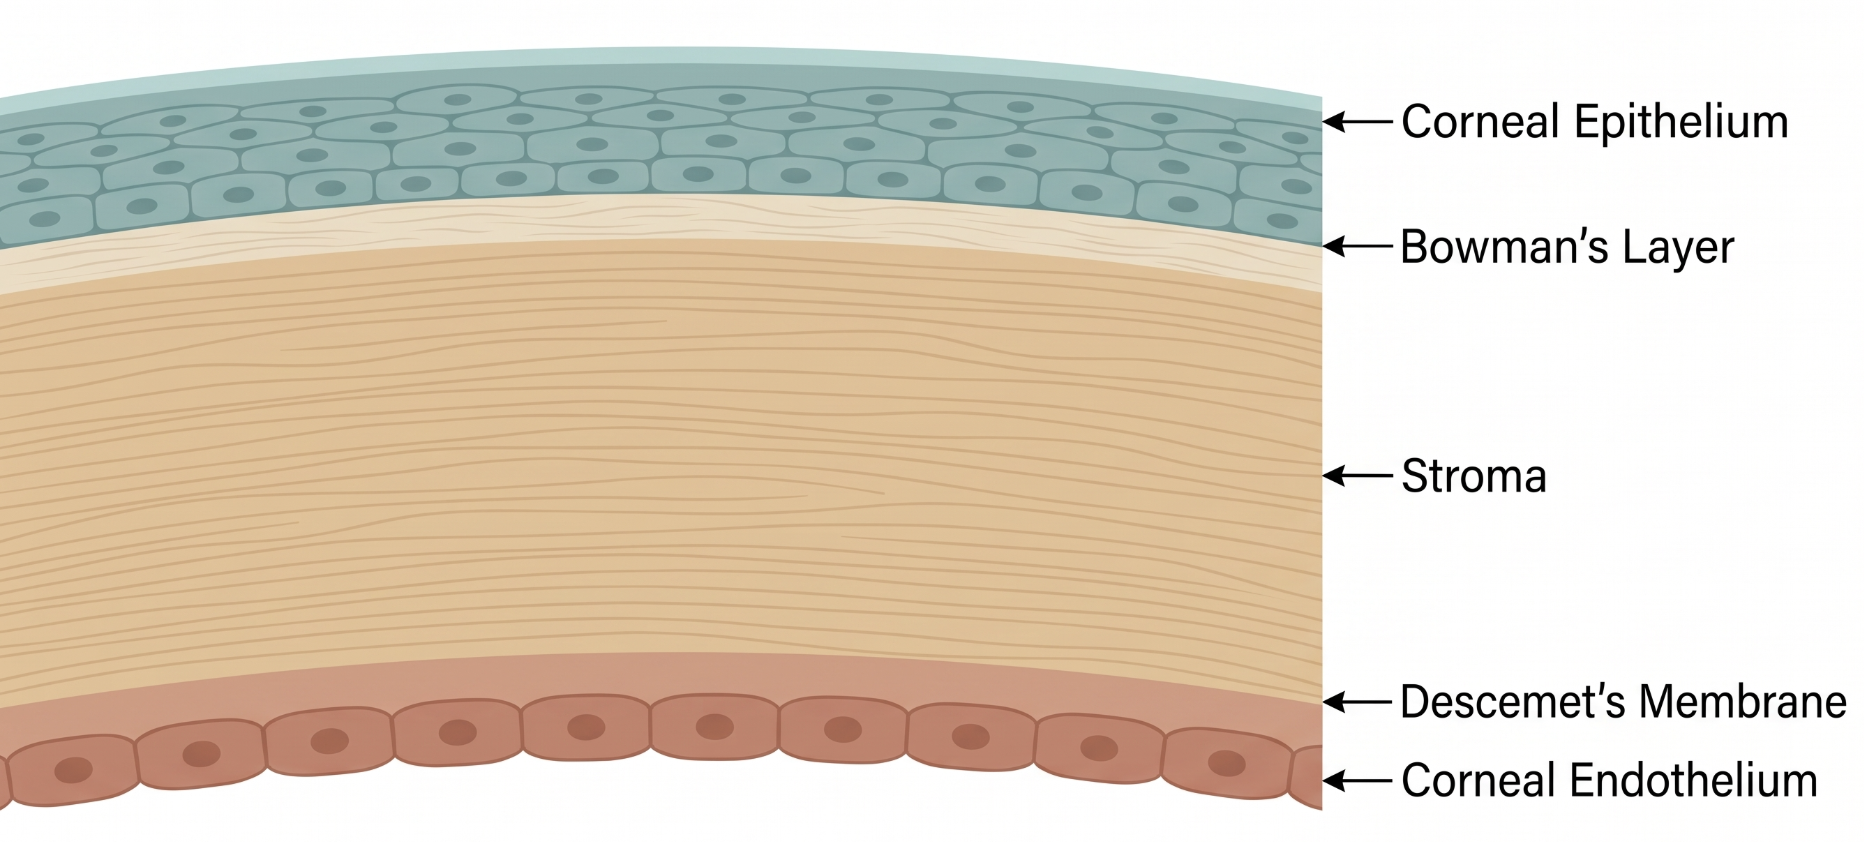
The corneal stroma makes up roughly 90% of corneal thickness and is organized into regularly arranged collagen lamellae. Filamentous fungi exploit this lamellar architecture, penetrating deeply along the stromal sheets — often well beyond the visible extent of the surface infiltrate. This is central to why fungal ulcers are notoriously difficult to eradicate medically.
Fungal keratitis is an aggressive, sight-threatening infection and a leading cause of corneal blindness in tropical and subtropical regions, caused most often by filamentous fungi (Fusarium, Aspergillus) or yeasts (Candida).2
Fungal organisms invade the stroma after an epithelial breach (trauma) or on a chronically compromised ocular surface. Filamentous fungi characteristically penetrate deeply along stromal lamellae, and fungal cell walls plus secreted proteases drive progressive stromal necrosis — explaining both the depth of tissue involvement and the difficulty of achieving medical cure in advanced cases.1
Patients present with pain, photophobia, redness, discharge, and decreased vision, often with a history of vegetative trauma, contact lens wear, or chronic ocular surface disease. Onset is often more indolent than bacterial keratitis, contributing to delayed diagnosis.
Suggestive exam findings include feathery/fuzzy branching infiltrate margins, satellite lesions, an elevated dry-appearing infiltrate surface, and a hypopyon disproportionately large relative to the surface infiltrate given deep stromal extension.
Differential diagnosis includes bacterial keratitis (more acute, more mucoid infiltrate, but substantial overlap), Acanthamoeba keratitis (radial perineural infiltrates, disproportionate pain), and herpetic stromal keratitis.
Diagnosis is challenging because clinical signs are often non-specific. Corneal scraping for KOH preparation and calcofluor white staining, combined with fungal culture on appropriate media, is standard; cultures should be held for at least 1–2 weeks given slower fungal growth compared with bacteria.1 In vivo confocal microscopy can identify fungal filaments non-invasively. PCR-based and molecular sequencing methods are increasingly used for atypical or rare organisms.3
Treatment is based on topical antifungal agents: natamycin (particularly effective for filamentous fungi like Fusarium) and voriconazole (broad-spectrum against filamentous fungi and yeasts, with good corneal penetration).1 Treatment is prolonged, often many weeks, with close monitoring for response.
For refractory or deep/severe cases, intracameral amphotericin B has emerging evidence of benefit as an adjunct — improved healing rates, shorter healing time, reduced hypopyon duration, and decreased need for keratoplasty — though the evidence base is primarily observational rather than randomized-trial-level.2 Therapeutic penetrating keratoplasty may be required in medically refractory cases.1
- Suspect fungal keratitis after vegetative/plant-matter trauma, especially with an indolent course not responding to antibacterial therapy
- Satellite lesions and a disproportionately large hypopyon both suggest a fungal rather than bacterial cause
- Fungal cultures grow slowly — hold cultures at least 1–2 weeks before calling them negative
- Common pitfall: using topical corticosteroids empirically before a fungal cause has been excluded, which can worsen fungal infection
- Common pitfall: underestimating the depth of stromal invasion based on the visible surface infiltrate alone
Suspecting and Working Up Fungal Keratitis
Clinical Skills for This Topic
Slit-lamp characterization of a corneal infiltrate →
Assess infiltrate margin (feathery vs. discrete), surface texture, satellite lesions, and hypopyon size relative to the visible infiltrate.
Corneal scraping technique
Obtain adequate material from the leading edge and base of the ulcer for KOH prep, calcofluor white stain, and culture on appropriate fungal media.
Directed trauma history-taking
Specifically ask about vegetative or plant-matter trauma, agricultural exposure, and contact lens hygiene, since these change pretest probability of a fungal cause.
Practice Questions
Question 1 of 6
Score: 0/0
What history should raise suspicion for fungal keratitis in a patient with a corneal ulcer?
Saved in this browser.
References
- [1]Bock R, et al. Mycotic Keratitis - Signs, Diagnosis, Therapy. Klinische Monatsblatter fur Augenheilkunde. 2025.
- [2]Chen KY, et al. Efficacy and safety of intracameral amphotericin B for fungal keratitis: A systematic review and meta-analysis. International Journal of Antimicrobial Agents. 2026.
- [3]Das S, et al. Emerging ocular pathogen: multidrug-resistant Corynespora cassiicola in fungal keratitis: case series and literature review. International Ophthalmology. 2025.