
Fuchs Endothelial Corneal Dystrophy
Curriculum lesson · updated 2026-07-29
Pending review from section expertOn this page
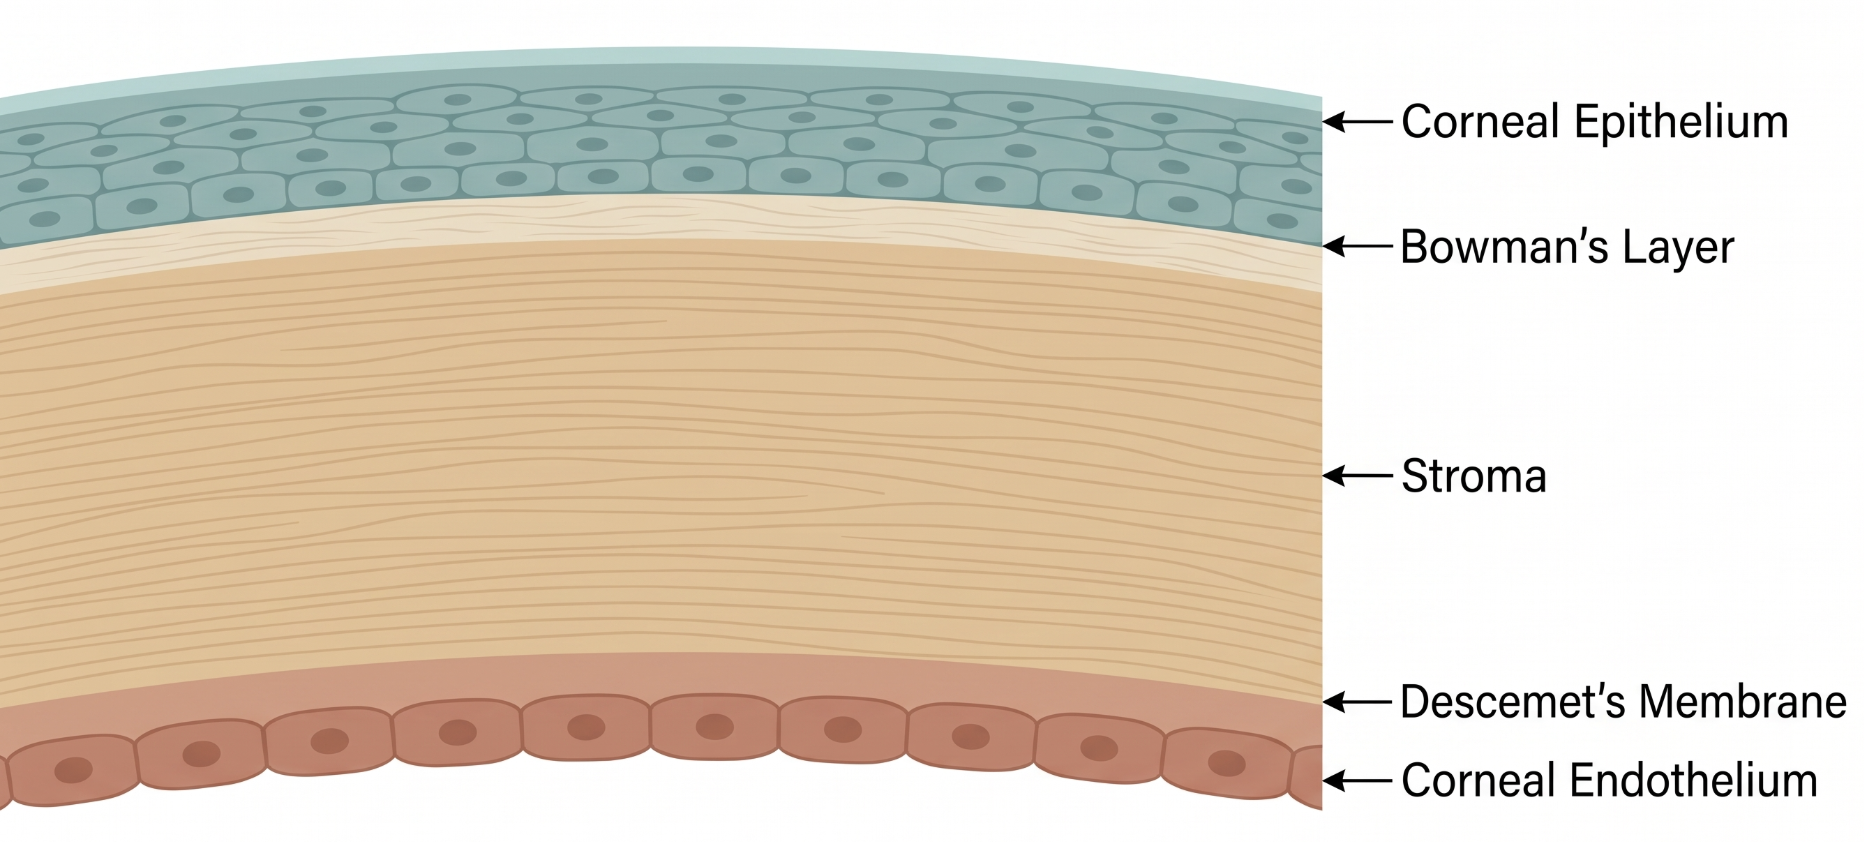
The corneal endothelium is a single, non-regenerating layer of cells lining the innermost surface of the cornea, sitting just posterior to Descemet's membrane. Its job is to actively pump fluid out of the stroma, keeping the cornea in a state of relative dehydration (deturgescence) necessary for transparency. Because these cells cannot divide to replace losses, endothelial cell density only ever decreases with age and disease.
Fuchs endothelial corneal dystrophy (FECD) is a progressive, bilateral disorder of accelerated endothelial cell loss and guttae formation on Descemet's membrane, ultimately leading to corneal edema and reduced vision, and is among the most common indications for corneal transplantation worldwide.2
In FECD, progressive endothelial cell loss and dysfunction — strongly associated with a CTG trinucleotide repeat expansion in the TCF4 gene in most cases — reduces the endothelium's fluid-pumping capacity below the threshold needed to keep the stroma dehydrated, leading to stromal and eventually epithelial edema once endothelial cell density falls critically low.1 Guttae, focal excrescences of abnormal collagen on Descemet's membrane, are an early visible marker of this dysfunction, often preceding clinically significant edema by years.
Early FECD is often asymptomatic, with guttae noted incidentally on slit-lamp exam. As endothelial function declines, patients report blurred vision characteristically worse in the morning (from overnight stromal fluid accumulation during lid closure) that improves through the day. Advanced disease produces persistent blur, glare, and pain when epithelial bullae rupture.
Differential diagnosis includes pseudophakic/aphakic bullous keratopathy (endothelial decompensation from surgical trauma rather than primary dystrophy — often clinically indistinguishable without surgical history), posterior polymorphous corneal dystrophy, congenital hereditary endothelial dystrophy (infancy onset), and myotonic dystrophy type 1, which can produce a mild corneal phenotype with guttae-like changes even without TCF4 repeat expansion.
Diagnosis is based on slit-lamp identification of guttae (best seen with specular reflection) plus supportive findings on pachymetry (increased central corneal thickness) and specular microscopy (reduced endothelial cell density, pleomorphism, polymegathism).
Early, asymptomatic disease is simply observed. Mild symptomatic disease (morning blur) can be managed with hypertonic saline drops or ointment, and a hairdryer held at arm's length on a cool setting to hasten evaporation of overnight edema.
For advanced disease with significant vision loss, Descemet membrane endothelial keratoplasty (DMEK) — selectively replacing only the diseased Descemet's membrane and endothelium — has become the preferred surgical treatment over full-thickness penetrating keratoplasty, offering faster visual recovery and lower rejection rates, though it carries a distinct learning curve and a risk of graft detachment requiring rebubbling.2 Common indications for DMEK include FECD, pseudophakic/aphakic bullous keratopathy, and prior graft failure.
- Guttae are often visible years before symptomatic edema develops — document and monitor even in asymptomatic patients
- Morning blur that improves through the day is a classic early FECD symptom, from overnight fluid accumulation during lid closure
- DMEK has become the preferred surgical approach over full-thickness keratoplasty for FECD, given faster recovery and lower rejection risk
- Common pitfall: attributing morning blur solely to dry eye or refractive fluctuation without examining for guttae and stromal edema
- Common pitfall: overlooking postoperative intraocular pressure elevation as a complication requiring monitoring after DMEK
Fuchs Dystrophy: From Guttae to DMEK
Clinical Skills for This Topic
Slit-lamp specular reflection technique →
Use specular reflection at the slit lamp to identify the characteristic 'beaten-metal' appearance of endothelial guttae.
Pachymetry interpretation (conceptual)
Understand that increased central corneal thickness reflects stromal edema from failing endothelial pump function.
Recognizing postoperative DMEK complications
Know to monitor for graft detachment (needing rebubbling) and elevated intraocular pressure in the postoperative period.
Practice Questions
Question 1 of 6
Score: 0/0
What is the primary function of the corneal endothelium that is lost in Fuchs endothelial corneal dystrophy?
Saved in this browser.
References
- [1]Viberg A, et al. TCF4 trinucleotide repeat expansion in Swedish cases with Fuchs' endothelial corneal dystrophy. Acta Ophthalmologica. 2021.
- [2]Borroni D, et al. Tips, Tricks, and Guides in Descemet Membrane Endothelial Keratoplasty Learning Curve. Journal of Ophthalmology. 2021.
- [3]Petrela RB, et al. Associations between measures of oestrogen exposure and severity of Fuchs endothelial corneal dystrophy. BMJ Open Ophthalmology. 2025.