
Eyelid & Orbital Anatomy
Curriculum lesson · updated 2026-07-30
Pending review from section expertOn this page
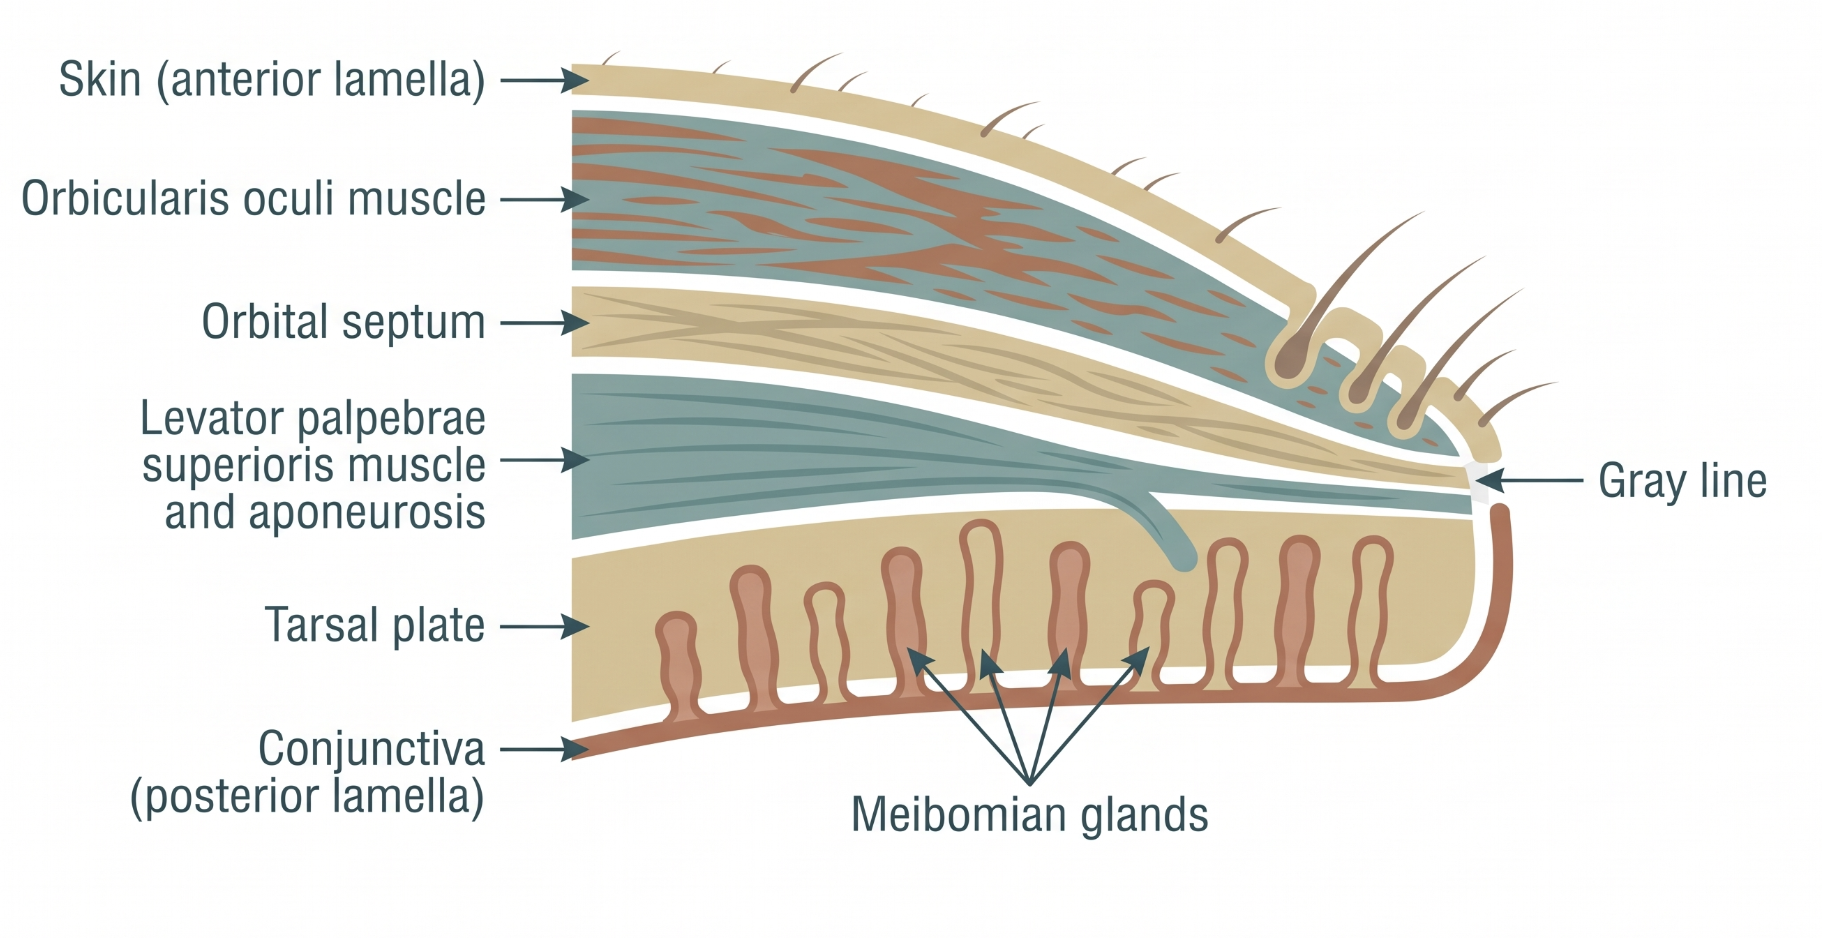
The eyelid is organized into anterior and posterior lamellae separated by the orbital septum. The anterior lamella consists of skin and orbicularis oculi (lid closure, CN VII); the posterior lamella consists of the tarsal plate (giving the lid margin its shape and rigidity) and palpebral conjunctiva. The orbital septum separates preseptal from postseptal (orbital) tissue — central to differentiating preseptal from orbital cellulitis. Lid elevation is provided by the levator palpebrae superioris (CN III) and, to a lesser degree, Müller's muscle (sympathetically innervated). The levator's aponeurosis inserts onto the anterior tarsal surface and skin. Surrounding its insertion is a complex, multilayered fibrous structure — including the preaponeurotic fat pad and a dense fibrous membrane enveloping it — that can itself transmit some of the levator's uplift force to the lid, rather than functioning purely as inert padding.1
Anatomic dissection shows the preaponeurotic fat pad is surrounded by a dense, multilayered fibrous membrane capable of transmitting the levator muscle's uplift force to the eyelid margin, rather than serving purely as structural cushioning.1 This has direct surgical relevance: advancing this fibrous membrane, with or without levator aponeurosis advancement, can correct mild-to-moderate blepharoptosis, particularly pseudoptosis from upper lid overloading.1 Separately, the superior fornix's check ligament connects anatomically to both the levator palpebrae superioris and the superior rectus muscle. Cadaveric study of lid-suspension surgery to this ligament suggests postoperative lid elevation reflects a synergistic mechanism combining static suspension force from the ligament with dynamic contraction force from both muscles, with the levator appearing to play the larger role.2
The bony orbit is a pyramidal socket formed by seven bones (frontal, zygomatic, maxillary, ethmoid, lacrimal, palatine, sphenoid), housing the globe, extraocular muscles, orbital fat, and neurovascular structures within the periorbita. The orbital floor and medial wall are notably thin and are the most common blow-out fracture sites after blunt trauma. The orbital apex is a tightly packed region through which the optic nerve, ophthalmic artery, and cranial nerves III, IV, V1, and VI pass — injury or compression here can produce apex syndrome affecting vision and multiple ocular motor nerves simultaneously.
Voluntary lid elevation depends on coordinated levator and Müller's muscle function; disruption of either — from aponeurotic dehiscence, neurogenic injury (CN III palsy), myogenic disease, or sympathetic dysfunction (Horner syndrome) — produces ptosis through mechanistically distinct pathways requiring different clinical evaluation. The orbital septum's integrity limits infection or hemorrhage confined anterior to it (preseptal) from spreading into the orbit proper (postseptal/orbital).
- The preseptal/postseptal distinction created by the orbital septum is the anatomic basis for differentiating preseptal from orbital cellulitis
- The preaponeurotic fat membrane's force-transmitting role explains why isolated fat/membrane advancement can correct select cases of mild ptosis without levator aponeurosis surgery1
- The thin orbital floor and medial wall explain why blow-out fractures preferentially occur at these sites rather than the thicker orbital rim
- The check ligament's dual connection to the levator and superior rectus explains why some lid-suspension procedures achieve elevation through combined static and dynamic forces2
- Ptosis can arise from aponeurotic, myogenic, neurogenic, or sympathetic (Horner) causes — each requires a different diagnostic approach
- The preaponeurotic fat pad is enveloped by a fibrous membrane capable of transmitting levator force to the lid margin, not inert padding1
- The orbital floor and medial wall are the thinnest orbital walls and the most common blow-out fracture sites
- The orbital apex crowds the optic nerve with multiple cranial nerves, so apex lesions can combine vision loss with multi-nerve ocular motor dysfunction
- Common pitfall: treating the preaponeurotic fat pad as purely structural padding rather than a force-transmitting anatomic structure1
- Common pitfall: overlooking the orbital septum as the anatomic boundary determining preseptal versus orbital spread of infection
- Common pitfall: generalizing single-study cadaveric lid-suspension measurements as universally applicable clinical thresholds rather than hypothesis-generating findings2
Eyelid Lamellae & the Orbital Septum Boundary
Clinical Skills for This Topic
Measuring MRD1 and levator function
Localize ptosis severity and help distinguish aponeurotic from myogenic or neurogenic causes.
Assessing extraocular movements and pupil in a patient with ptosis or orbital trauma →
Screen for CN III involvement or orbital apex syndrome when ptosis accompanies motility or pupillary changes.
Distinguishing preseptal from orbital signs on exam
Check for proptosis, restricted/painful motility, or acuity change indicating true postseptal (orbital) involvement.
Practice Questions
Question 1 of 6
Score: 0/0
What separates the anterior and posterior lamellae of the eyelid?
Saved in this browser.
References
- [1]Zhao H, Zhang Y, Wijaya WA, Chen Z, Song F, Fan W, Zeng L, Zhao Z, Zhang Z, Li Z. Not Merely an Enveloping Membrane: Anatomy of the Preaponeurotic Fat Membrane and Its Role in Blepharoptosis Correction. Aesthetic Plastic Surgery. 2026.
- [2]Zhuang W, Yang C. Surgical Mechanism of Suspension of the Eyelid to the Check Ligament of the Superior Fornix for Blepharoptosis: An Anatomical Study. Aesthetic Plastic Surgery. 2026.