
Cornea Anatomy & Physiology
Curriculum lesson · updated 2026-07-30
Pending review from section expertOn this page
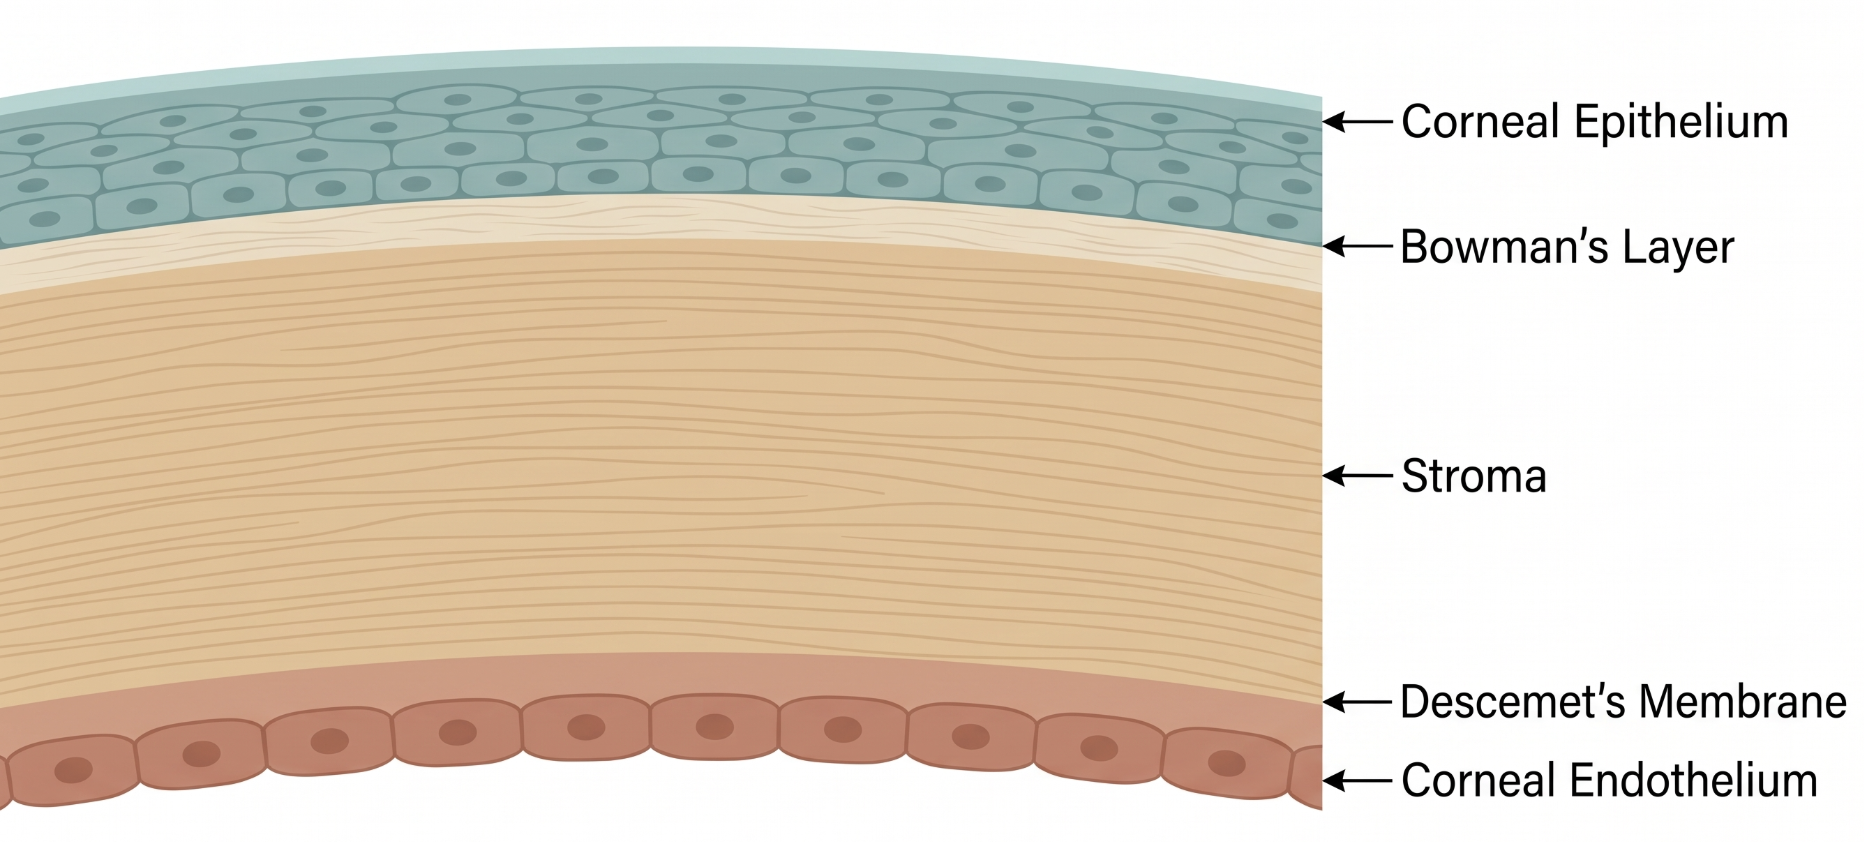
The cornea is the eye's clear, avascular, dome-shaped anterior window, providing roughly two-thirds of the eye's total refractive power. It has five histologically distinct layers, from anterior to posterior: epithelium, Bowman's layer, stroma, Descemet's membrane, and endothelium.1 The epithelium is a stratified, non-keratinized squamous layer that continuously regenerates from limbal stem cells at the corneoscleral junction. Bowman's layer is an acellular collagen condensation that resists trauma but does not regenerate if damaged. The stroma makes up roughly 90% of corneal thickness, built from precisely stacked collagen lamellae with regularly spaced fibrils. Descemet's membrane is the thick, elastic basement membrane of the endothelium, and the endothelium itself is the innermost monolayer, located distal to Descemet's membrane and adjacent to the aqueous-filled anterior chamber.1
Corneal endothelial cell shape is maintained by an apical band of actin filaments, with cadherin-based junctional complexes forming the barrier between adjacent cells and extending to the basolateral borders.1 This barrier, together with active fluid transport, regulates stromal hydration. Human corneal endothelial cells have essentially no capacity for regeneration after injury or age-related loss — remaining cells enlarge and spread (polymegathism/pleomorphism) to cover gaps rather than dividing to replace lost cells.1 This non-regenerative property is why endothelial cell density is closely monitored before and after intraocular surgery.
Corneal transparency depends on the stroma's deturgescence — its relatively dehydrated, precisely ordered state — actively regulated by fluid transport connected to the endothelium.1 The endothelium continuously pumps fluid out of the stroma against its natural tendency to imbibe water and swell, counterbalancing a constant passive leak of aqueous across the endothelial barrier. When endothelial cell density falls below a critical threshold, the pump cannot keep pace with the leak, and the stroma swells, disrupting collagen spacing and causing corneal edema and, when severe, painful epithelial bullae.1
The cornea is also one of the most densely innervated tissues in the body. Sensory nerve fibers (predominantly from the ophthalmic division of the trigeminal nerve) form a sub-basal nerve plexus beneath the epithelium, supporting epithelial, stromal, and endothelial integrity; modulating tear secretion; and mediating the blink reflex and pain sensation essential for protecting the ocular surface.2
Corneal endothelial cell density declines gradually and irreversibly over a normal lifetime, and because these cells cannot regenerate, this decline accelerates the point at which surgery or trauma can tip a cornea into decompensation.1 Corneal nerves also undergo progressive attrition and morphologic change with age, driven by processes similar to aging elsewhere in the body (oxidative stress, mitochondrial dysfunction, low-grade inflammation).2 This age-related nerve loss reduces trophic support to the epithelium, delays wound healing, and predisposes to dry eye disease, neurotrophic keratopathy, and reduced corneal sensation after surgery — further accelerated by diabetes, chronic contact lens wear, topical preservative exposure, and herpes zoster ophthalmicus.2 Unlike the epithelium, corneal nerves have only limited regenerative capacity and do not reliably return fully to baseline after significant injury.2
- Endothelial cell density is measured before intraocular surgery because the endothelium cannot regenerate — a low count raises the risk of postoperative corneal decompensation
- Loss of corneal sensation (herpetic disease, diabetes, prior refractive/corneal surgery) predisposes to neurotrophic keratopathy through impaired epithelial trophic support
- Stromal collagen's precise spacing, not its absence, makes the cornea transparent — scarring disrupts this order and causes opacity regardless of collagen quantity
- Limbal stem cell deficiency (chemical injury, contact lens overwear, limbal disease) impairs epithelial regeneration and can cause persistent epithelial defects or conjunctivalization
- The corneal endothelium does not regenerate in humans — cell loss is permanent and cumulative over a lifetime1
- Transparency depends on active endothelial fluid pumping against a constant passive leak, not on the absence of stromal water content
- The sub-basal nerve plexus links corneal sensation to epithelial health — nerve loss and epithelial disease often occur together
- The cornea is avascular, so its nutrition and immune surveillance depend on the tear film, aqueous humor, and limbal blood supply rather than direct vascularization
- Common pitfall: assuming corneal endothelial cells can regenerate after significant loss, the way epithelial cells do
- Common pitfall: overlooking reduced corneal sensation as a clue to an underlying process rather than an isolated incidental finding
- Common pitfall: forgetting that age-related corneal nerve degeneration, not just tear volume, contributes to dry eye and delayed healing in older patients2
Corneal Layers & the Endothelial Fluid Pump
Clinical Skills for This Topic
Slit-lamp examination of corneal layers and clarity →
Localize pathology to a specific layer (epithelial defect, stromal scar, endothelial guttae/edema) to guide diagnosis.
Assessing corneal sensation
Screen for neurotrophic changes in patients with prior herpetic disease, diabetes, or corneal surgery.
Recognizing signs of endothelial decompensation on exam
Identify stromal haze, epithelial bullae, or a thickened, edematous cornea suggesting the endothelial pump can no longer keep pace with fluid leak.
Practice Questions
Question 1 of 6
Score: 0/0
What are the five layers of the cornea, from anterior to posterior?
Saved in this browser.
References
- [1]Pai DN, Srinivas SP, Shetty A. Exploring corneal endothelial cell dynamics: structure, functions and therapeutic approaches. Molecular Biology Reports. 2025.
- [2]Niktinat H, Alviar M, Kashani M, Massoumi H, Djalilian AR, Jalilian E. Aging and Corneal Nerve Health: Mechanisms of Degeneration and Emerging Therapies for the Cornea. Cells. 2025.