
Aqueous Humor Dynamics & Anatomy
Curriculum lesson · updated 2026-07-30
Pending review from section expertOn this page
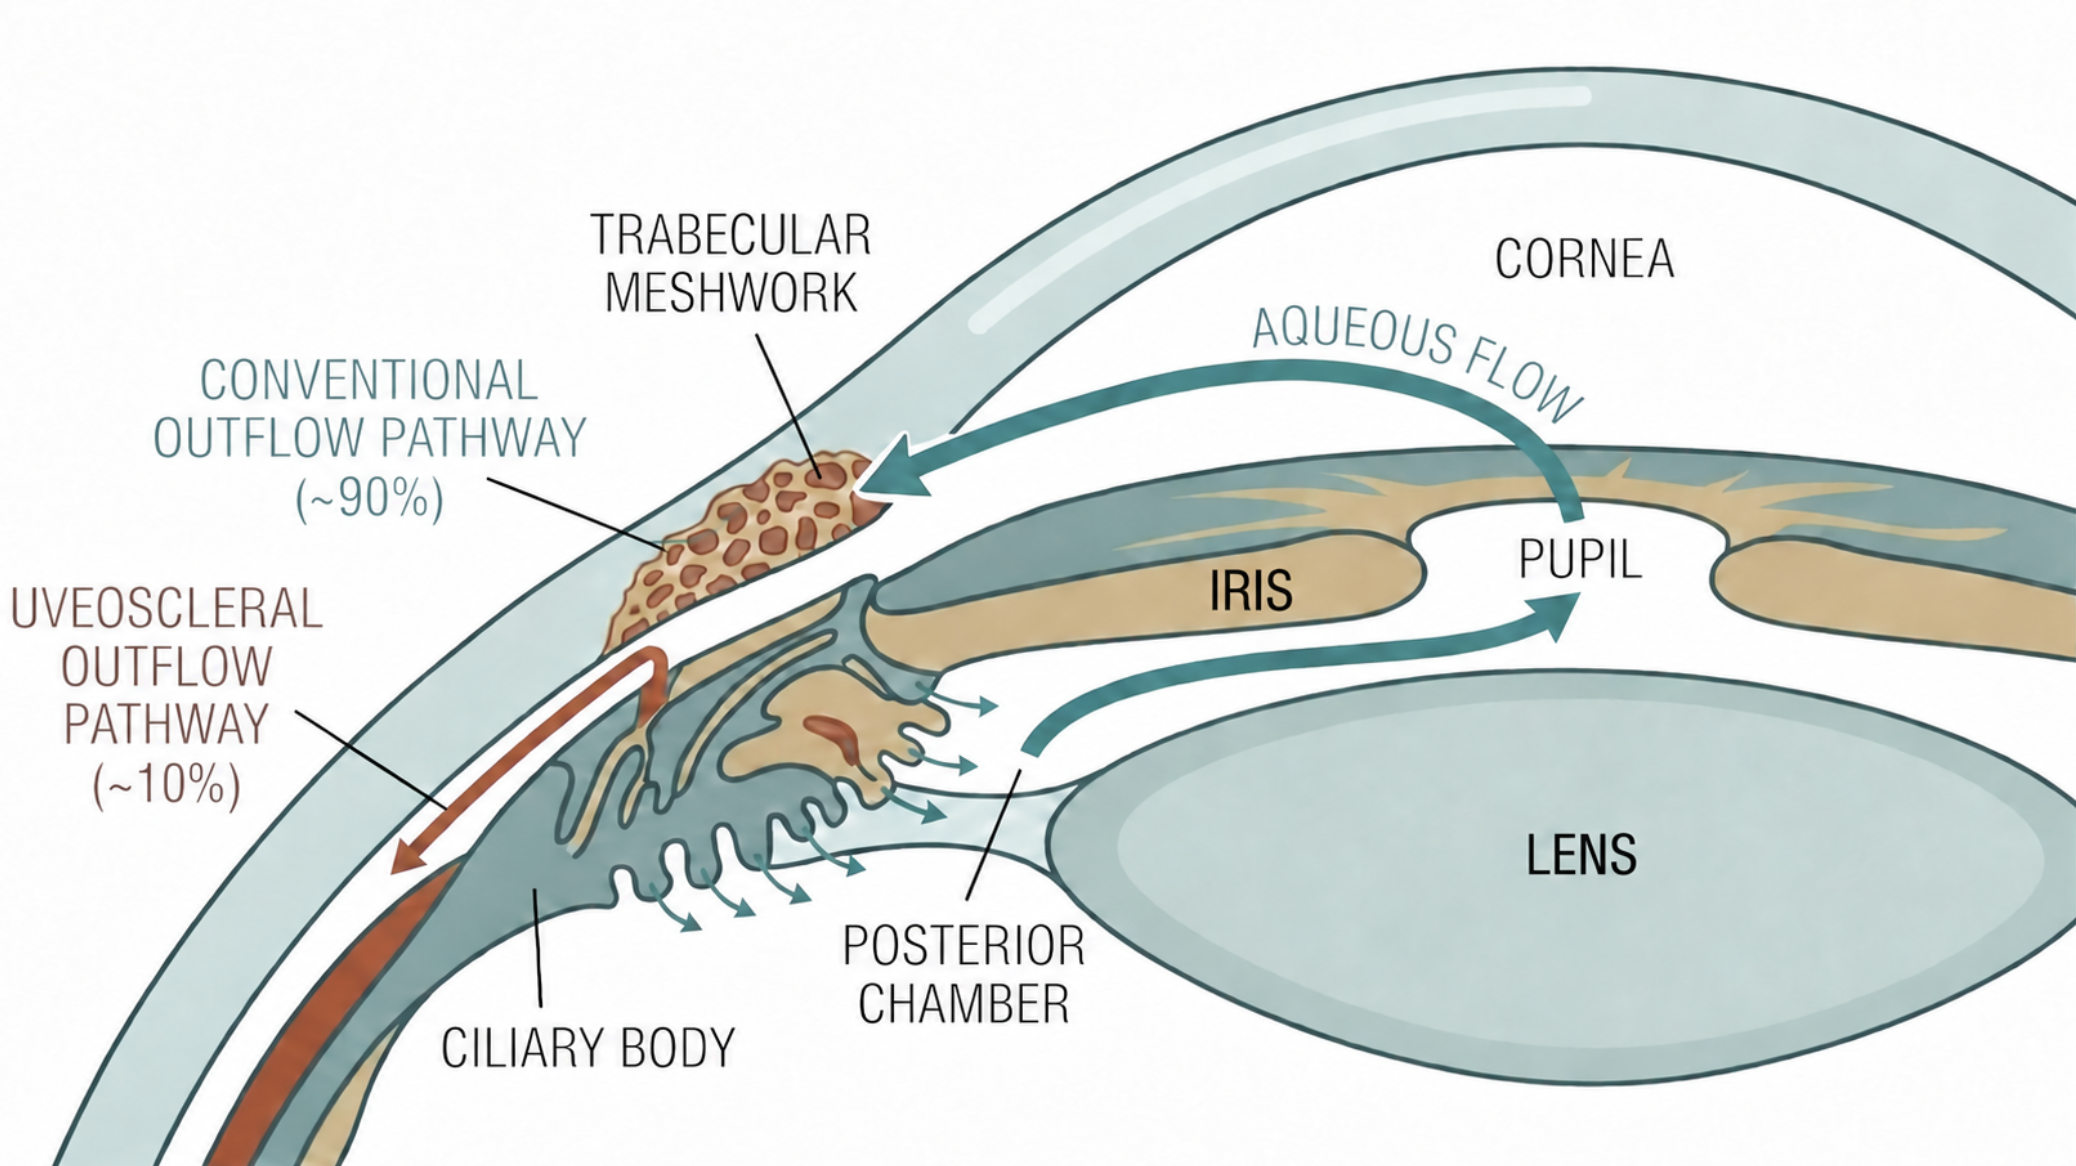
Aqueous humor is secreted by the ciliary processes of the pars plicata, the folded, highly vascularized anterior portion of the ciliary body. From the posterior chamber it flows around the lens equator, through the pupil, into the anterior chamber, reaching the anterior chamber angle — the junction between peripheral cornea and iris root, bordered by the trabecular meshwork. Two outflow pathways then carry aqueous out of the eye. The conventional (trabecular) pathway routes aqueous through the trabecular meshwork into Schlemm's canal, then collector channels and the episcleral venous system, accounting for the majority of outflow and behaving in a pressure-dependent way — resistance rises as IOP rises.1 The unconventional (uveoscleral) pathway instead carries aqueous through the ciliary muscle into the suprachoroidal space and out through the sclera, and is largely pressure-independent.1
The trabecular meshwork is a three-dimensional, sieve-like tissue spanning the angle, with the innermost juxtacanalicular (cribriform) layer adjacent to Schlemm's canal's inner wall generating most of the pathway's outflow resistance. Trabecular meshwork and Schlemm's canal endothelial cells are contractile, and their cytoskeletal tone directly affects flow resistance.2 The Rho GTPase/Rho-kinase (ROCK) signaling pathway centrally regulates this contractility, controlling actomyosin-based tension and extracellular matrix remodeling in the trabecular meshwork and Schlemm's canal; dysregulation of this pathway increases aqueous outflow resistance, a major contributor to glaucoma.2
Aqueous production combines ultrafiltration and active, energy-dependent secretion (via ciliary epithelial Na⁺/K⁺-ATPase) across the ciliary processes' double-layered epithelium — the physiologic basis exploited by drug classes that suppress production, such as beta-blockers and carbonic anhydrase inhibitors. IOP reflects the balance between continuous inflow and outflow resistance across the two drainage pathways; most day-to-day IOP regulation happens through changes in conventional outflow resistance rather than production rate. Because Rho/ROCK signaling governs trabecular meshwork and Schlemm's canal contractility, pharmacologically modulating this pathway (Rho kinase inhibitors) lowers outflow resistance directly at its anatomic source, with emerging neuroprotective properties independent of IOP-lowering.2
Because the conventional and uveoscleral pathways are anatomically and functionally distinct, glaucoma surgery is best understood as a mechanism-based menu targeting specific points along this anatomy.1 Trabecular bypass, goniotomy, trabeculotomy, and canaloplasty enhance conventional outflow at the trabecular meshwork/Schlemm's canal level and are most appropriate when this can achieve meaningful pressure reduction, typically in mild-to-moderate open-angle glaucoma.1 Subconjunctival filtration (trabeculectomy) and aqueous shunt surgery instead create an entirely new outflow route bypassing the natural pathways, remaining necessary when a lower target pressure is required, particularly in advanced or rapidly progressive disease.1 Lens extraction and ciliary-body-directed procedures further illustrate how surgical strategy is matched to disease phenotype and anatomical mechanism rather than applied uniformly.1
- The trabecular meshwork's juxtacanalicular layer, adjacent to Schlemm's canal, generates most of the conventional pathway's outflow resistance
- Aqueous outflow occurs through two anatomically distinct routes: a pressure-dependent conventional pathway and a largely pressure-independent uveoscleral pathway1
- Trabecular meshwork/Schlemm's canal contractility, governed by Rho/ROCK signaling, is itself a modifiable target for IOP-lowering therapy2
- Modern MIGS procedures are best understood by which specific outflow pathway component they target, not as one homogeneous category1
- Common pitfall: treating all glaucoma surgeries as interchangeable rather than recognizing each targets a distinct point in outflow anatomy1
- Common pitfall: assuming IOP is regulated solely by aqueous production rate, when day-to-day regulation is dominated by outflow resistance changes
- Common pitfall: overlooking the uveoscleral pathway as a therapeutic target since it responds differently than the pressure-dependent conventional pathway
Aqueous Humor Flow: Production to Outflow
Clinical Skills for This Topic
Goldmann applanation tonometry →
Measure IOP as the clinically actionable readout of the balance between aqueous production and outflow resistance.
Gonioscopy to visualize the anterior chamber angle
Directly assess trabecular meshwork visibility and angle anatomy, the structural basis for the conventional outflow pathway.
Correlating IOP-lowering drug class with its anatomic target
Match beta-blockers/carbonic anhydrase inhibitors (reduce production) versus prostaglandin analogs (increase uveoscleral outflow) to the underlying aqueous dynamics being modulated.
Practice Questions
Question 1 of 6
Score: 0/0
Where is aqueous humor produced, and what is one physiologic basis exploited by glaucoma medications that reduce its production?
Saved in this browser.
References
- [1]Luboń W, Smędowski A, Dorecka M. Precision Glaucoma Surgery: A Mechanism-Based Review of MIGS and Contemporary Surgical Pathways. Journal of Clinical Medicine. 2026.
- [2]Raghavan S, Pattabiraman PP. Rho GTPase and Rho Kinase Signaling in Tissue Contractility and Intraocular Pressure Regulation. Frontiers in Bioscience (Landmark Edition). 2026.