
Allergic Conjunctivitis
Curriculum lesson · updated 2026-07-29
Pending review from section expertOn this page
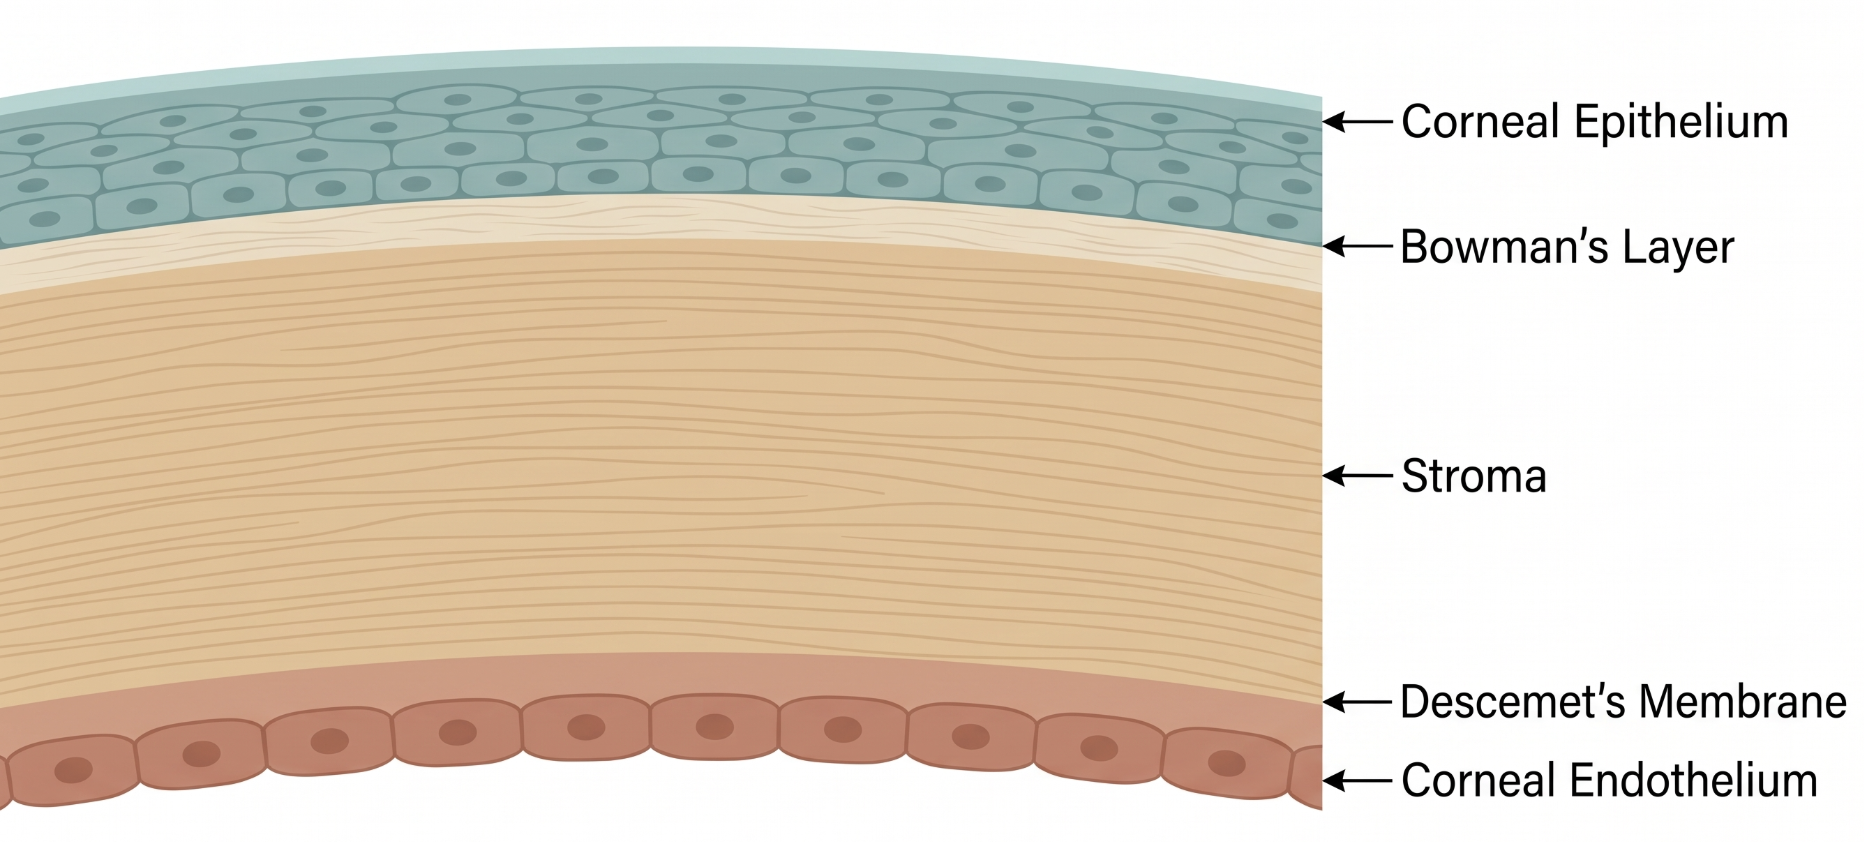
The conjunctiva's dense population of mast cells and lymphoid tissue, especially along the upper tarsal conjunctiva, makes it a primary site for IgE-mediated hypersensitivity reactions. The tarsal conjunctiva's papillary architecture is where the giant papillae ("cobblestoning") of severe allergic disease develop, and the limbus — the corneoscleral junction — is where the eosinophil-rich Horner-Trantas dots of vernal keratoconjunctivitis (VKC) appear.
Allergic eye disease affects an estimated 15–40% of people worldwide and ranges from mild seasonal/perennial allergic conjunctivitis to sight-threatening VKC and atopic keratoconjunctivitis (AKC) with corneal involvement.1
Allergic eye disease arises when environmental (or, in giant papillary conjunctivitis, mechanical) triggers cause IgE-mediated mast cell degranulation, releasing histamine and other mediators that produce itching, hyperemia, and chemosis.1 Chronic forms — VKC and AKC — involve additional mixed type I, IVa, and IVb hypersensitivity pathways with eosinophil- and T-cell-driven tissue remodeling, which is why they, unlike simple seasonal allergic conjunctivitis, can produce corneal shield ulcers and limbal changes.2
Itching is the hallmark symptom across all forms and the single most useful feature distinguishing allergic from infectious conjunctivitis. Presentation is typically bilateral.
- Seasonal/perennial allergic conjunctivitis: itching, watery discharge, mild injection, fine papillary reaction tracking with allergen exposure
- VKC: intense itching, thick ropy discharge, photophobia, giant papillae ("cobblestoning") on the upper tarsus, limbal Horner-Trantas dots — typically young males, improves around puberty
- AKC: chronic itching, thickened/macerated lid skin, papillary reaction, higher risk of corneal scarring and cataract than VKC — linked to atopic dermatitis, persists into adulthood
- Giant papillary conjunctivitis: contact lens intolerance, mucous discharge, giant papillae, typically less itching than VKC/AKC
Differential diagnosis includes adenoviral conjunctivitis (watery but follicular, preauricular node, less itch), bacterial conjunctivitis (purulent, papillary, minimal itch), dry eye disease, blepharitis, and contact dermatitis from topical drops or cosmetics.
Diagnosis is primarily clinical, based on history and slit-lamp exam.1 Ancillary allergy testing (skin prick or serum IgE) is reserved for unclear or refractory cases, or when identifying a specific avoidable allergen would change management.
Management is stepwise1:
1. Allergen avoidance, cool compresses, preservative-free lubricants for all severities 2. Topical antihistamines or combined antihistamine/mast-cell stabilizers for mild-moderate disease 3. Short courses of topical corticosteroids for flares, particularly in VKC/AKC 4. Topical calcineurin inhibitors (cyclosporine, tacrolimus) for steroid-sparing long-term control in VKC/AKC3 5. Emerging monoclonal antibody and small-molecule therapies for refractory severe disease1
For GPC, the key intervention is addressing the mechanical trigger — improved lens hygiene, more frequent replacement, or temporary discontinuation — alongside topical anti-allergy therapy.
- Itching is the single most useful symptom for distinguishing allergic from infectious conjunctivitis
- A corneal shield ulcer in a child with itchy eyes and giant papillae should prompt consideration of VKC, not infectious keratitis
- Chronic eye rubbing in allergic eye disease is a recognized keratoconus risk factor — counsel patients to avoid rubbing
- Common pitfall: treating allergic conjunctivitis with topical antibiotics, which have no role absent secondary infection
- Common pitfall: long-term topical steroid use without monitoring for steroid-related glaucoma or cataract
Itchy Red Eye: Sorting Out Allergic Eye Disease
Clinical Skills for This Topic
Slit-lamp examination of the tarsal conjunctiva →
Evert the upper eyelid to inspect for giant papillae and cobblestoning, and check the limbus for Horner-Trantas dots.
Fluorescein staining for corneal shield ulcer
In severe VKC, look for a sterile epithelial defect from mechanical trauma of giant papillae — a sight-threatening finding requiring aggressive treatment.
Directed allergy/atopy history
Ask about eye rubbing, seasonal pattern, contact lens wear, and personal/family history of asthma, eczema, or allergic rhinitis.
Practice Questions
Question 1 of 6
Score: 0/0
What symptom is most useful for distinguishing allergic conjunctivitis from infectious conjunctivitis?
Saved in this browser.
References
- [1]Naik MU, et al. Allergic eye disease in clinical practice: essential updates for eye care professionals. Clinical & Experimental Optometry. 2026.
- [2]Bogacka E, et al. Ocular Allergy Within the Framework of the EAACI Nomenclature of Allergic Diseases and Hypersensitivity Reactions. Allergy, Asthma & Immunology Research. 2026.
- [3]Leonardi A, et al. The effects of the COVID-19 pandemic on the treatment of allergic eye diseases. Current Opinion in Allergy and Clinical Immunology. 2021.